CAR-T Cell Therapy
CAR-T Cell Therapy: Engineering the Immune System for Precision Oncology
CAR-T (Chimeric Antigen Receptor T-cell) Cell Therapy represents a ground-breaking milestone in precision oncology and cellular biotechnology. Known as a revolutionary "living drug," this cutting-edge immunotherapy involves harvesting a patient’s own T-cells, re-engineering them in a high-tech laboratory to express specific cancer-targeting receptors, and re-infusing them to hunt down and eliminate resistant cancer cells with sub-cellular precision.
How the Technology Works: Genetic Engineering & Reprogramming
The creation of CAR-T cells follows a multi-step bioengineering process that transforms standard white blood cells into targeted, cancer-destroying agents:
T-Cell Isolation (Leukapheresis): White blood cells are extracted from the patient’s bloodstream using specialized automated blood-separator platforms.
Genetic Re-Engineering: In a certified cellular laboratory, a viral vector introduces a synthetic gene into the T-cells, instructing them to produce Chimeric Antigen Receptors (CARs) on their cell surfaces.
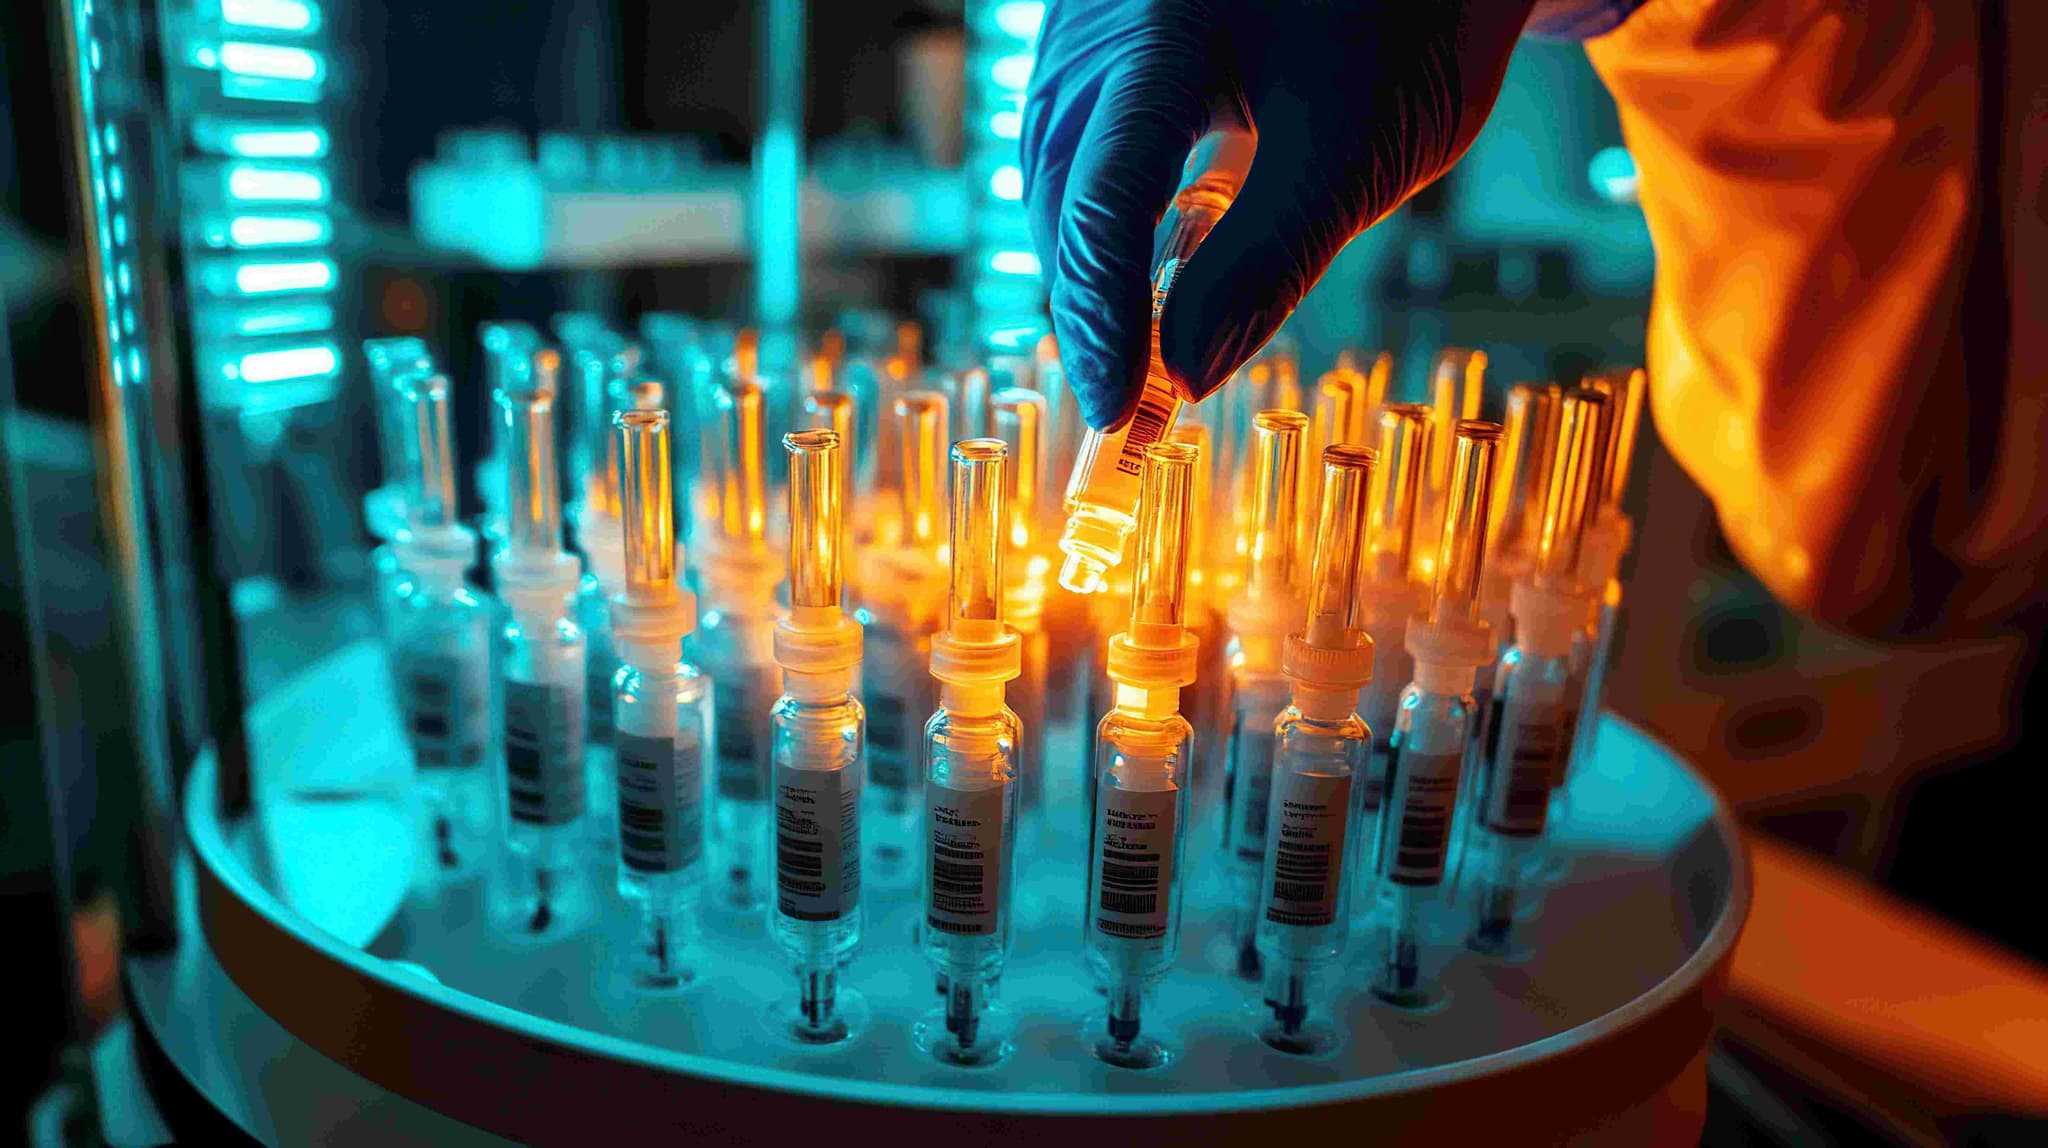
Bioreactor Expansion: The newly modified CAR-T cells are cultured and multiplied by the millions in a strictly controlled environment to generate a high-potency "cellular army".
Targeted Re-Infusion: Following a short course of lymphodepleting conditioning chemotherapy, the personalized CAR-T cell product is infused back into the patient to identify and destroy target tumor antigens.
Key Clinical Applications in Advanced Hematology & Oncology
CAR-T cell therapy has redefined clinical outcomes for patients facing hard-to-treat or refractory blood cancers where conventional regimens have failed:
Relapsed/Refractory B-Cell Malignancies: Delivers high complete remission rates in relapsed B-cell Acute Lymphoblastic Leukemia (B-ALL) and Diffuse Large B-Cell Lymphoma (DLBCL).
Multiple Myeloma Targeted Care: Targets B-Cell Maturation Antigens (BCMA) to treat relapsed or treatment-resistant multiple myeloma.
Next-Generation Solid Tumor Research: Ongoing global clinical trials are adapting CAR-T platforms with dual-targeting vectors to treat complex solid tumors.
Engineering Advantages, Cost & Patient Benefits
By bridging molecular biology with bedside care, CAR-T cell therapy offers substantial clinical efficacy and significant financial advantages for international patients:
Cost Efficiency & Indigenous Innovation: While commercial CAR-T cell therapy costs between $375,000 and $550,000+ in the US and Western Europe, patients accessing approved therapies (such as home-grown NexCAR19 or international products) in top-tier Indian medical centers incur total costs of approximately $40,000 to $85,000—delivering up to 80% to 85% cost savings.
Targeted Molecular Specificity: CAR-T cells are programmed to bind exclusively to tumor antigens (such as CD19 or BCMA), drastically reducing non-specific toxicity compared to systemic chemotherapy.
Long-Term Immunological Persistence: Once infused, CAR-T cells actively multiply and remain in the patient’s body as a form of long-term biological surveillance against cancer recurrence.
Single-Dose Therapeutic Paradigm: Administered as a single targeted infusion rather than prolonged, repetitive chemotherapy cycles, minimizing overall hospital stays and physical exhaustion.
Frequently Asked Questions (FAQs)
How does CAR-T cell therapy different from a bone marrow transplant (BMT)?
A bone marrow transplant replaces a patient's damaged marrow with healthy donor stem cells to rebuild the blood system. In contrast, CAR-T therapy uses the patient's own immune T-cells, genetically modified in a laboratory to specifically attack and destroy targeted cancer cells.
How long does the CAR-T treatment process take?
The entire cycle takes approximately 3 to 6 weeks. T-cell collection (apheresis) takes a single day, followed by 2 to 4 weeks of laboratory manufacturing and quality testing. The actual infusion takes less than an hour, followed by 1 to 2 weeks of close inpatient monitoring.
What are the main risks associated with CAR-T cell therapy?
The primary known reaction is Cytokine Release Syndrome (CRS), an inflammatory response that occurs as CAR-T cells rapidly multiply and attack cancer cells. Specialized cellular units manage these immune responses using dedicated protocols and targeted anti-cytokine therapies.